Breastfeeding

Learning outcomes
Introduction
Breastfeeding is the most natural and optimal form of nutrition for neonates and infants. The benefits are:
The World Health Organization (WHO) recommends continued breastfeeding up to two years of age or beyond, with exclusive breastfeeding advocated for the first six months. To minimize the risk of allergic sensitization and celiac disease—particularly in infants with an atopic family history—the European Society for Paediatric Gastroenterology, Hepatology and Nutrition (ESPGHAN) advises introducing complementary foods between 17 and 26 weeks of life (4–6 months). Early initiation of non-milk complementary feeding within this window may also be considered in cases of failure to thrive or faltering growth (suboptimal weight gain).
Nutrition
The intake of macronutrients and micronutrients varies depending on gestational age, clinical condition, and type of nutrition. While macronutrients (carbohydrates – sugars; proteins; lipids – fats) primarily determine the energy provision of metabolism (daily requirement in g/kg), micronutrients (electrolytes, trace elements, water- and fat-soluble vitamins) are essential for homeostasis (daily requirement in mg/kg or µg/kg).
Enteral nutrition should ensure adequate qualitative and quantitative growth of the child—average weight gains during the first year of life reflect the growth dynamics of neonates and infants: first 3 months (25–30 g/day), 3–6 months (20 g/day), 6–9 months (15 g/day), and 9–12 months (10 g/day).
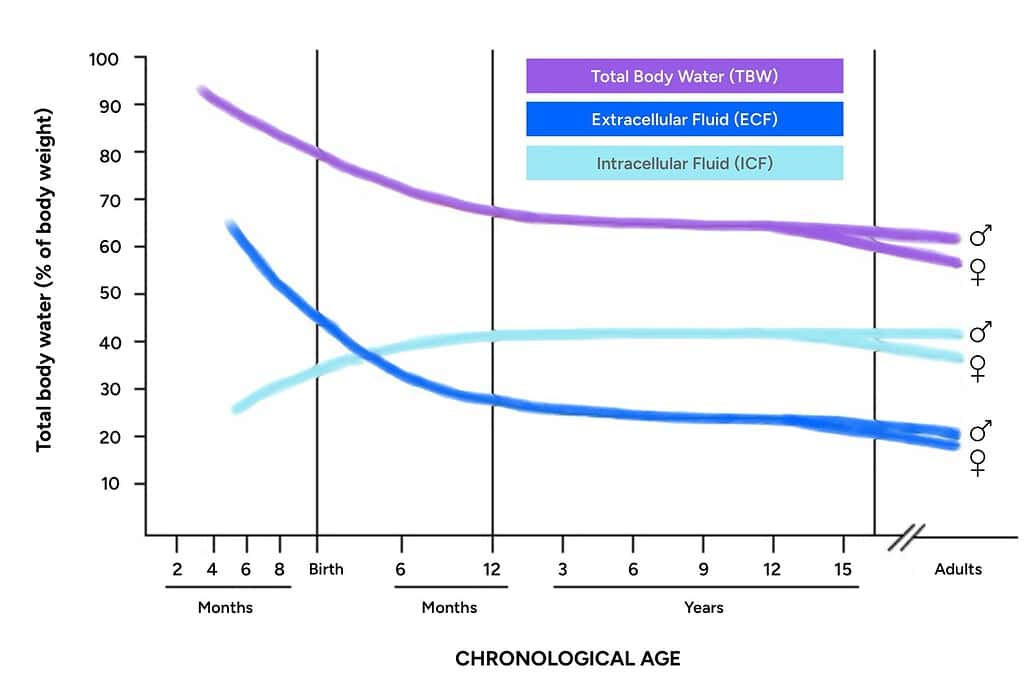
Related to this is daily total fluid intake (TFI), which is high in neonates and infants, decreases with age, and reflects total body water as a proportion of weight—for example, extremely preterm infants have a significantly greater proportion of body water (90%) relative to body weight compared to term infants (75%) or adults (50%). Furthermore, neonates and young infants have a relatively higher proportion of extracellular fluid (ECF) compared to intracellular fluid (ICF). With age, the relative proportion of ECF decreases—according to some hypotheses, the higher proportion of ECF in neonates serves as a temporary water reservoir to compensate for delayed onset of lactation.
In neonates, a certain degree of postnatal weight loss is natural. Generally, the more preterm the neonate, the greater the weight loss that may occur (very low birth weight infants: 7–10%; term infants: 3–7%, depending on the neonate’s trophic status and feeding modality). Weight loss of up to 10% of birth weight within the first week of life can be considered physiological even in a term infant, provided it does not cause clinical issues.
Diagnosis
A marked reduction in ECF volume (negative fluid balance) can lead to cardiovascular compromise, metabolic imbalances, and clinical worsening. The baseline physical examination and blood workup can help us to assess homeostasis and severity of malnutrition or dehydration.
Clinical findings
Typical signs of dehydration in newborns:
Laboratory investigations
Breastfeeding
Physiology
During pregnancy, elevated estrogen levels stimulate glandular proliferation and structural breast tissue development. Following delivery, prolactin mediates postnatal milk synthesis (lactogenesis). Infant suckling triggers the release of oxytocin, which causes the myoepithelial cells surrounding the alveoli to contract and propel milk into the ductal network—the milk ejection (let-down) reflex. Anatomically, breast milk travels sequentially from the alveolar lobules through the lactiferous ducts into the lactiferous sinuses (ampullae) before delivery to the infant.
Proper technique and mother-child cooperation are essential for successful breastfeeding. Effective breastfeeding depends on proper infant positioning supported by innate neonatal reflexes—specifically the rooting, sucking, and swallowing reflexes. Feeding should be conducted on demand (typically every 2–3 hours) to promote and sustain maternal lactation, with simultaneous feeding (tandem nursing) fully feasible for twins.
Human milk
The composition of breast milk is complex and changes dynamically with the infant’s postnatal age (colostrum, mature milk). In addition to water, it contains a wide array of nutritional and non-nutritional components:
Colostrum is a thick yellowish milk produced for the first few days after birth (highly enriched with immunoglobulins). There are several times more lipids in the hindmilk (milk at the end of a feed) than in the foremilk (milk at the beginning of a feed). Interestingly, protein is the most stable part of breast milk with 70% of whey proteins (mainly lactalbumin) and 30% of casein protein. On the contrary, in the animal milk (sheep, buffalo, cow) casein can constitute up to 80% of total protein content.
|
COMPOSITION |
COLOSTRUM |
MATURE MILK |
|---|---|---|
|
Energy (kcal/100ml) |
54 |
67 |
|
Protein (g/100 ml) |
2 |
1 |
|
Lipids (g/100 ml) |
1.8 |
3.4 |
|
Lactose (g/100 ml) |
5.6 |
6.5 |
|
Calcium (mg/100 ml) |
21 |
25 |
|
Phosphate (mg/100 ml) |
11 |
14 |
|
Sodium (mg/100 ml) |
33 |
20 |
|
Potassium (mg/100 ml) |
62 |
46 |
|
Zinc (mg/100 ml) |
0.9 |
0.15 |
|
Iron (mg/100 ml) |
0.12 |
0.09 |
Adequate lactation ensures baseline nutritional and energy intake for a term neonate: protein (1.5–2 g/kg/day), fat (3 g/kg/day), carbohydrates (10 g/kg/day), and energy for basal metabolism (50–70 kcal/kg/day) and growth (100–110 kcal/kg/day), respectively. The goal is birth weight regain by day 6–10 of life, followed by a subsequent growth phase (≥ day 11 of life) monitored during routine visits with the primary care pediatrician via anthropometry (weight, length, head circumference) and growth charts.
In exclusively breastfed infants, enteral vitamin D supplementation (prevention of rickets) is recommended at a dose of 400–600 IU of vitamin D₃ starting from the second week of life. Vitamin D represents a group of fat-soluble secosteroids that function biologically as prohormones rather than traditional dietary vitamins. The two principal physiologically active isoforms are vitamin D₂ (ergocalciferol) and vitamin D₃ (cholecalciferol).
All newborns should receive vitamin K after birth. The efficacy of oral administration (2 mg vitamin K) for the prevention of early and classic forms of vitamin K deficiency bleeding (VKDB) is comparable to intramuscular administration. However, for late-onset VKDB, oral prophylaxis may be insufficient (particularly in exclusively breastfed infants). The intramuscular route provides effective prevention against all forms of VKDB while concurrently eliminating the risks posed by potential occult conditions (e.g., malabsorption).
Contraindications
In certain cases, breastfeeding and nutrition with maternal milk are contraindicated.
Lactation problems
In certain cases, factors exist that lead to difficult or inadequate lactation. Anatomical-physiological risk factors on the maternal side:
Medical-social risk factors on the maternal side:
Anatomical-physiological risk factors on the infant side:
Medical-social risk factors on the infant side:
Baby friendly initiative
Baby Friendly Hospital Initiative (BFHI) is a worldwide programme of the World Health Organization (WHO) and United Nations International Children’s Emergency Fund (UNICEF) to promote and encourage breastfeeding across the globe. There are 10 steps for successful breastfeeding according to BFHI, however, several critical reports pointed out the potential drawbacks of the programme, including rigid enforcement of the practices, increased risk for Sudden Unexpected Postnatal Collapse (SUPC), unnecessary pacifier ban and maternal exhaustion.
Critical management procedures:
Key clinical practices:
Formula feeding
If breastfeeding is not possible or maternal milk supply is insufficient, an appropriate alternative must be selected in the form of a standard infant formula (breast milk substitute). These are categorized into infant formula (from birth, designated as stage 1) and follow-on formula (from 4–6 months of age, designated as stage 2).
For specific patient populations, specialized formulas are indicated:
Conclusion
Breastfeeding is the most natural method of infant feeding. If breastfeeding is contraindicated or maternal milk is insufficient, nutrition must be provided using standard or specialized infant formula. In the event of inadequate enteral intake, parenteral nutrition is necessary to meet metabolic demands and ensure adequate growth.