

Neonatal Respiratory Distress

Learning outcomes
Introduction
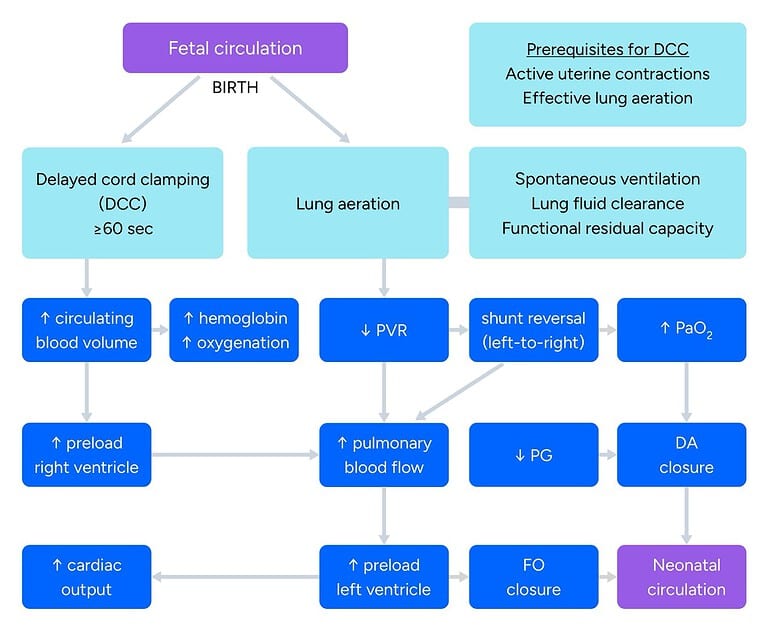
Successful postnatal transition depends on a rapid cascade of physiological milestones:
When any part of this process falters, neonatal respiratory distress develops—clinically defined by any change to frequency and/or quality of breathing pattern (i.e. abnormal breathing rates or increased work of breathing). A normal neonatal respiratory rate is 40-60 breaths/min, characterised by quiet and unlabored breathing.
However, during the first hours after birth (the immediate postnatal adaptation period), transient rates up to 60-70 breaths/min can occasionally be observed without distress, but rates consistently >60 breaths/min (tachypnea) or accompanied by signs of respiratory distress signal pathology.
Postnatal adaptation
Spontaneous respiratory effort and the establishment of FRC drives a rapid rise in arterial partial pressure of oxygen (PaO2) in the pulmonary vasculature (3 kPa → 10 kPa) within minutes, dramatically reducing pulmonary vascular resistance (PVR).
Together with the reversal of ductal shunting across the ductus arteriosus (right-to-left → left-to-right), this markedly enhances pulmonary perfusion, left ventricular preload, and cardiac output. These physiological transitions can be further augmented by delayed cord clamping (DCC), which increases circulating blood volume, improves myocardial contractility, and optimizes tissue oxygen delivery.
When postnatal adaptation is impaired, neonatal respiratory distress develops—defined as an alteration in the character and/or frequency of breathing. Neonatal respiratory distress remains one of the most common indications for neonatal intensive care unit (NICU) admission.
While often apparent immediately after delivery, symptoms may also develop later during hospitalization or following discharge home. For practical and didactic clarity, etiologies of neonatal respiratory compromise are broadly classified into pulmonary and extrapulmonary causes.
Risk factors
Diagnosis
Physical examination (inspection, auscultation) and the measurement of peripheral oxygen saturation via pulse oximetry (SpO2) form the cornerstone of initial assessment. In the immediate postnatal period, the pulse oximeter probe is preferentially placed on the right upper extremity (wrist or palm) to measure preductal saturation.
Clinical findings
Typical signs of neonatal respiratory distress:
Newborns with respiratory distress relatively often present with circulatory or systemic signs:
Laboratory investigations
Imaging modalities
Differential diagnosis
Pulmonary causes of neonatal respiratory distress:
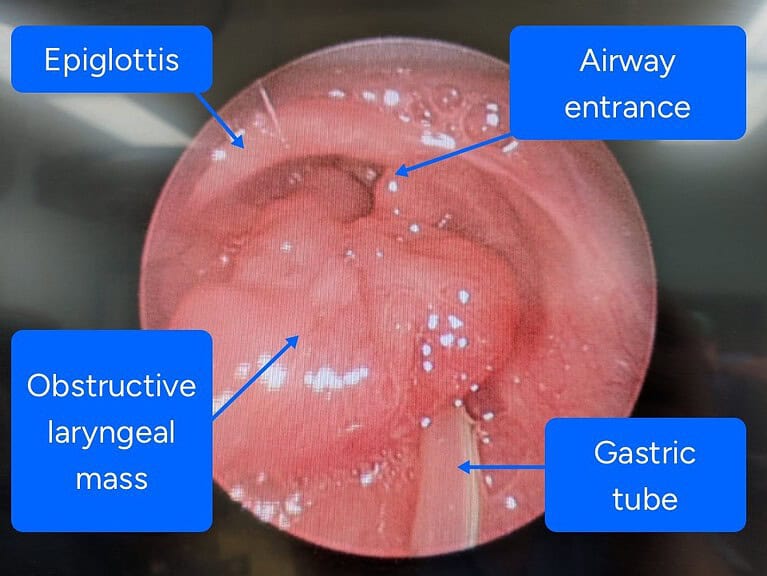
Extrapulmonary causes of neonatal respiratory distress:
Therapy
General therapy
Oxygen therapy
Continuous monitoring of peripheral oxygen saturation via pulse oximetry (SpO2) enables precise titration of oxygen therapy, helping prevent both hypoxia (esp. cerebral hypoxia) and hyperoxia (retinopathy). Supplemental medical gas must be actively warmed and humidified before delivery to protect neonatal airway mucosa and prevent heat loss. Delivered oxygen concentration is defined by the fraction of inspired oxygen (FiO2), ranging from 0.21 (21% oxygen, equivalent to ambient air) up to 1.0 (100% oxygen).
Home oxygen therapy (low flow oxygen through nasal cannulas) is indicated for stable, recovering neonates with bronchopulmonary dysplasia (BPD) to facilitate early discharge while supporting sustained growth and neurodevelopment.
Ventilatory support
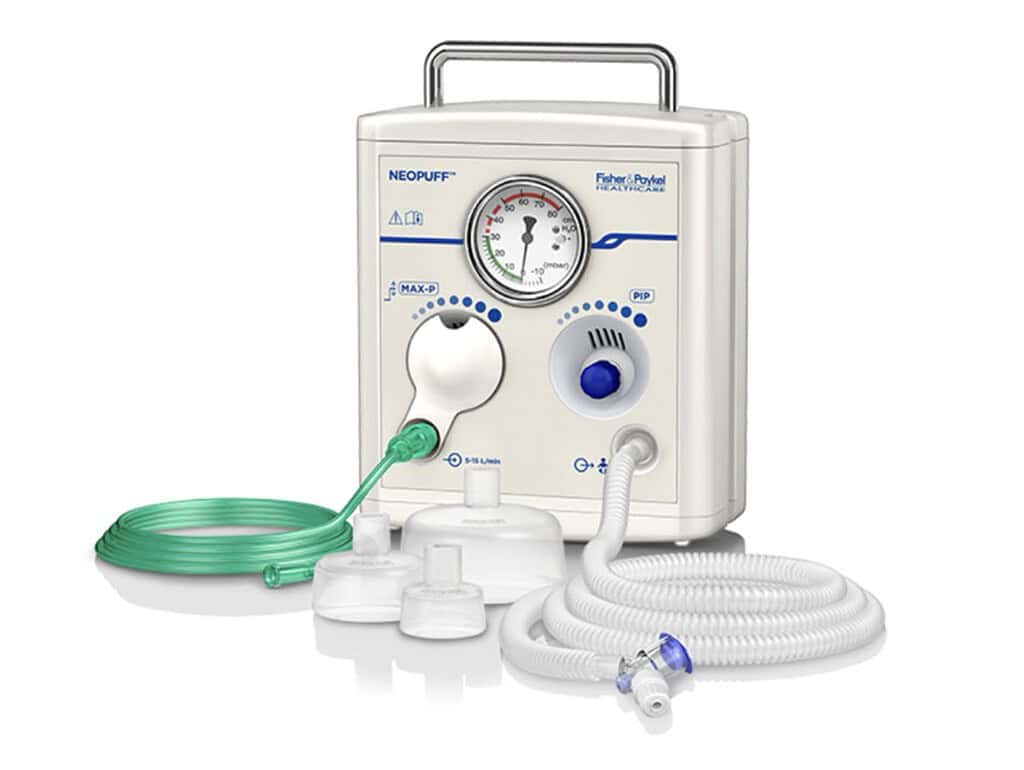
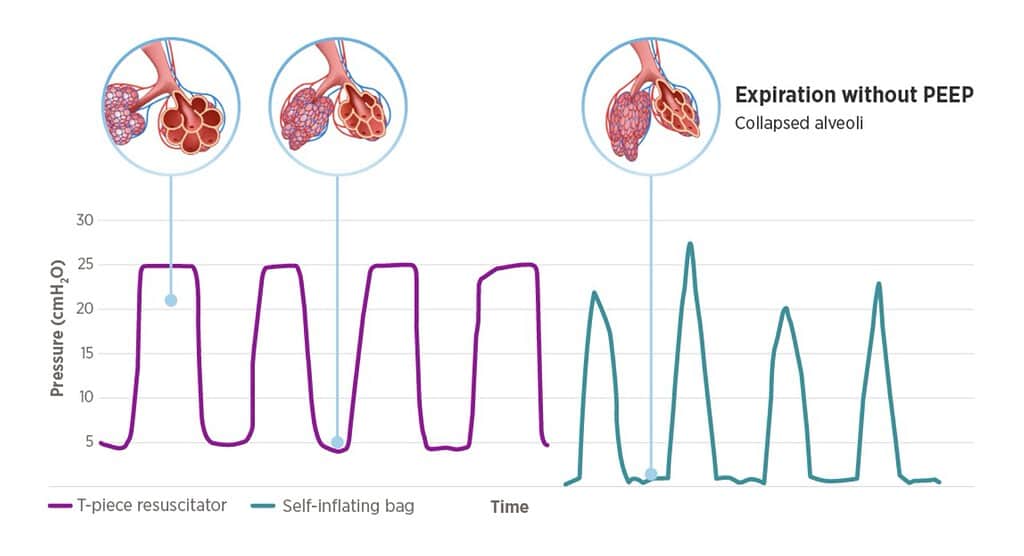
Currently, when a newborn experiences compromised postnatal adaptation with signs of respiratory distress, a T-piece resuscitator (e.g., Neopuff) is most commonly used, offering several advantages over conventional bag-valve-mask resuscitation. Compared to self-inflating and flow-inflating bags, T-piece resuscitators (using facial masks or nasal interfaces) provide better-controlled, more consistent peak inspiratory pressure (PIP) alongside reliable positive end-expiratory pressure (PEEP), thereby helping protect the neonatal lungs.
Invasive (mechanical) ventilatory support requires endotracheal intubation, utilizing either conventional or unconventional (high-frequency oscillation) ventilation modes. Employing synchronized ventilation modes (e.g., SIMV, SIPPV, PSV) combined with volume guarantee (VG) delivers more consistent tidal volumes, significantly reducing the risk of volutrauma and barotrauma (air-leak syndromes) and severe grades of intraventricular hemorrhage (IVH) in preterm neonates.
Surfactant
Surfactant is a surface-active agent that lowers surface tension, stabilizes alveoli against end-expiratory collapse, and improves pulmonary compliance. Type II pneumocytes begin producing surfactant around 22–24 weeks of gestation and are also responsible for its subsequent reabsorption and recycling for reuse.
Surfactant storage pools differ dramatically between term and preterm neonates (100 mg/kg vs. 5 mg/kg). Surfactant is composed of approximately 85% phospholipids (dipalmitoylphosphatidylcholine, phosphatidylcholine, phosphatidylglycerol) and 10% specific proteins (SP-A,B,C,D).
In more severe courses of respiratory distress syndrome, exogenous pulmonary administration is necessary (e.g., poractant alfa / Curosurf 200 mg/kg—a natural surfactant obtained from porcine lung lavage). This therapeutic agent can also be administered in cases of secondary surfactant inactivation or dysfunction (e.g., congenital pneumonia, meconium aspiration syndrome, or pulmonary hemorrhage).
Surfactant administration can be performed via several methods:
Specific therapy
Additional therapeutic options by etiology of neonatal respiratory distress:
Pulmonary causes
Respiratory Distress Syndrome (RDS)
The original term hyaline membrane disease reflected the postmortem histopathological findings within the pulmonary alveoli of deceased preterm neonates (intra-alveolar leakage of proteins and fluid created deposits of amorphous/hyaline material lining the alveolar spaces). The syndrome is defined by functional and anatomical pulmonary immaturity (surfactant deficiency, inability to maintain FRC, muscle hypotonia), with its incidence increasing inversely with gestational age.
Clinical signs of RDS typically develop and progress within the first hours of life, carrying a risk of life-threatening complications (acute respiratory failure, air-leak syndromes). It presents as homogeneous pulmonary involvement with a classic “ground-glass” appearance on plain chest radiography—symmetrical reticulogranular markings (microatelectasis interspersed with foci of hyperinflation) and diffuse decreased lung inflation and translucency, which may progress to a complete “white-out” appearance.
RDS requires ventilatory support, oxygen therapy, and other supportive modalities (see Therapy). Regarding ventilatory management, non-invasive continuous positive airway pressure (nasal CPAP) represents the primary initial intervention. In more severe or progressive courses, exogenous surfactant replacement and potential invasive mechanical ventilation (MV) become necessary.
Transient Tachypnea of the Newborn (TTN)
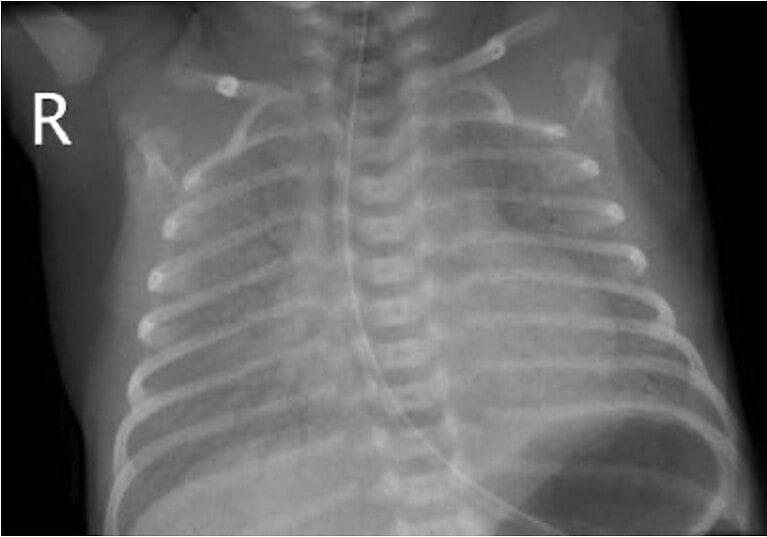
The condition is caused by delayed peripartum clearance and reabsorption of fetal lung fluid into pulmonary capillary and lymphatic vascular beds, which is why it is sometimes referred to as “wet lung” syndrome. Impaired gas exchange efficiency leads to increased work of breathing and tachypnea (auscultation reveals bilateral moist crackles/rales).
TTN typically occurs in term or late preterm infants (gestational age 34+0–36+6 weeks) delivered via cesarean section (particularly without prior onset of labor) and in the presence of additional risk factors (perinatal hypoxia, maternal diabetes mellitus). The prognosis is favorable, and management in milder cases may be limited to observation, continuous monitoring or supplemental oxygen therapy with clinical resolution within 24–48 hours.
More severe presentations may necessitate ventilatory support and persist for approximately 3–7 days. The differential diagnosis requires ruling out other etiologies of respiratory distress (infection, pneumothorax, MAS, or RDS).
Meconium Aspiration Syndrome (MAS)
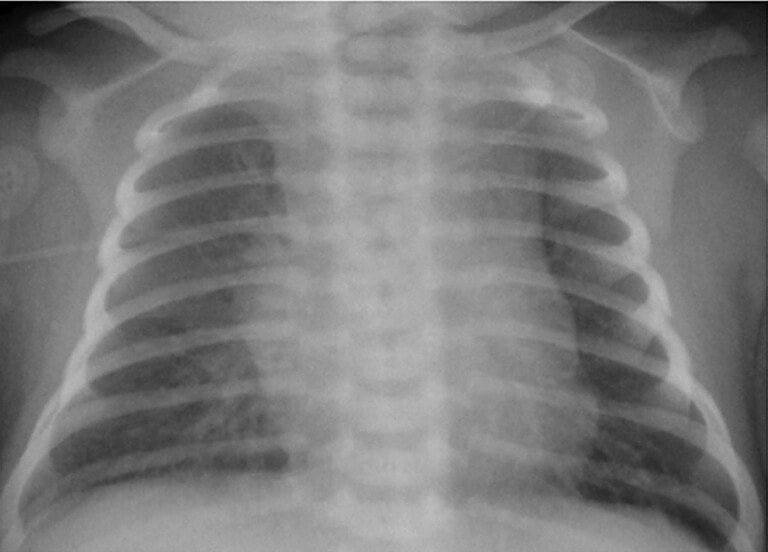
Perinatal hypoxia can trigger meconium passage into the amniotic fluid and gasping (deep, irregular breaths). This may lead to the aspiration of meconium-stained amniotic fluid or pure meconium, occurring predominantly in term and post-term neonates. Tachydyspnea and progressive hypoxemia develop immediately after delivery, requiring ventilatory support and oxygen therapy.
The radiographic appearance is characterized by coarse, patchy (focal) infiltrates with areas of reduced lung aeration/transparency. A more severe course of MAS involves secondary surfactant dysfunction, lung inflammation and the potential development of PPHN – requiring mechanical ventilation, surfactant administration, antibiotics and circulatory support.
Pneumonia
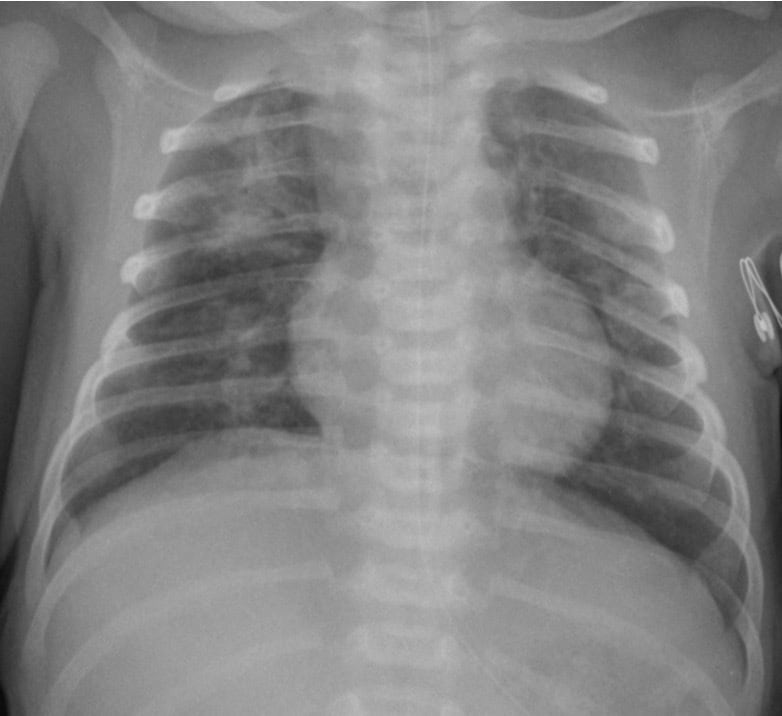
Infectious complications can arise during the early-onset period (chorioamnionitis, aspiration of infected amniotic fluid leading to congenital pneumonia) or the late-onset neonatal period (hematogenous dissemination or pathological airway colonization during prolonged mechanical ventilation). Etiological agents include GBS (Streptococcus agalactiae), Gram-negative bacilli (e.g., E. coli or Klebsiella pneumoniae), and atypical pathogens (Ureaplasma urealyticum/parvum).
Clinical presentation and radiographic findings often mimic MAS. Pulmonary inflammation triggers secondary surfactant inactivation and dysfunction, precipitating PPHN. When compounded by neonatal sepsis, this cascade leads to acute combined respiratory and circulatory failure. Comprehensive management requires multimodality support: invasive mechanical ventilation, surfactant replacement, selective pulmonary vasodilation with inhaled nitric oxide. An integral component of therapy is intravenous antibiotic coverage initiated immediately following cultures and microbiological sampling.
Air leak syndromes
This category encompasses several clinical entities—pneumothorax, pulmonary interstitial emphysema (PIE), pneumomediastinum, and pneumopericardium. Air-leak syndrome (extravasation of air outside the physiological tracheobronchial tree) can complicate neonatal respiratory distress arising from primary pulmonary etiologies (RDS, MAS, pneumonia) or develop during mechanical ventilation with uncontrolled tidal volumes (ventilator settings, delivery room resuscitation).
Asymmetric auscultatory and radiographic/ultrasound findings are characteristic. While a rim/mantle pneumothorax may resolve spontaneously, a tension pneumothorax presents with sudden bradycardia and desaturation (risk of circulatory collapse and asystole) and mandates urgent intervention – needle decompression in the 2nd–3rd intercostal space in the midclavicular line or chest tube placement (thoracostomy in the 4th–6th intercostal space in the anterior axillary line; FR 8/10 tube).
Bronchopulmonary Dysplasia (BPD)
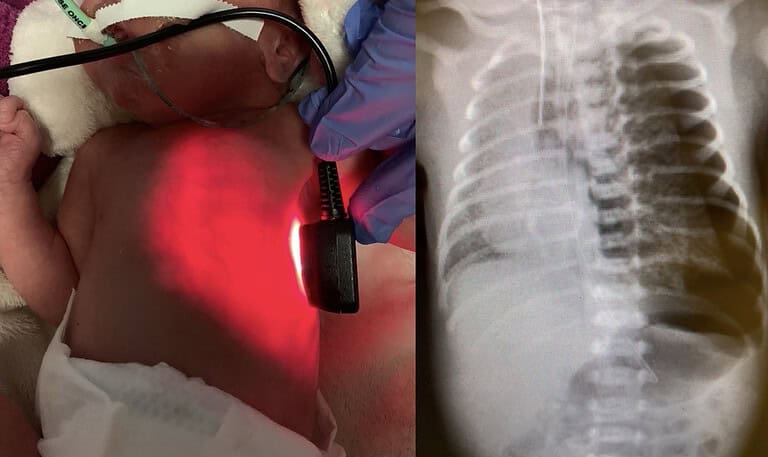
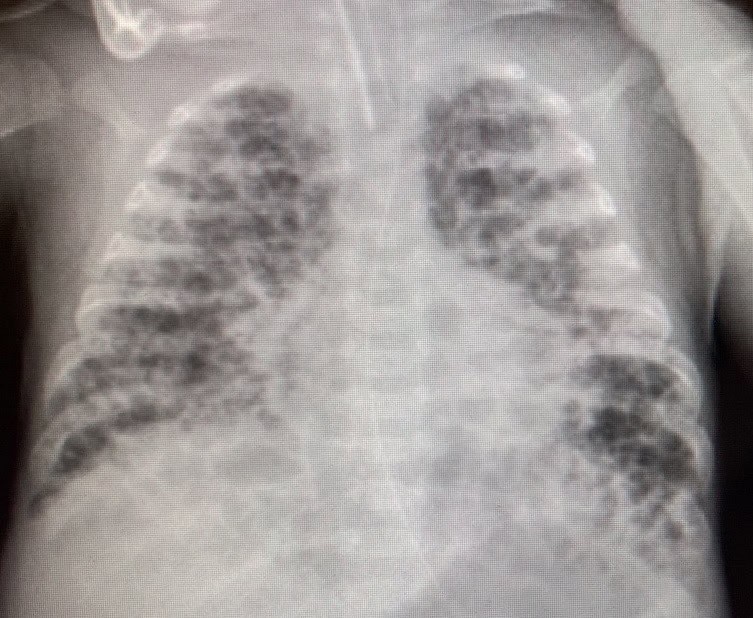
BPD is a multifactorial, chronic lung disease occurring primarily in preterm infants born at <32 weeks of gestation. The exposure of immature, vulnerable lung tissue to multiple insults (infection, oxygen toxicity, mechanical ventilation, malnutrition) results in a characteristic clinical and radiographic presentation – heterogeneous pulmonary involvement with diffusely reduced aeration/translucency and focal areas of alternating hyperinflation/emphysema and atelectasis.
BPD is a restrictive lung disease characterized by pulmonary fibrosis (expansion of interstitial connective tissue) alongside arrested alveolarization and dysregulated vascularization. Currently, the Jensen classification is widely utilized, defining BPD severity based on the mode of ventilatory support (regardless of supplemental oxygen concentration) at 36 weeks postmenstrual age. This classification is not only relatively simple, but it also best predicts early childhood respiratory morbidity.
|
BPD GRADE |
VENTILATORY SUPPORT |
|---|---|
|
0 |
No ventilatory support |
|
1 |
Nasal cannula with flow ≤2 L/min (low flow) |
|
2 |
Nasal cannula with flow >2 L/min (high flow) |
|
3 |
Invasive mechanical ventilation |
Management is comprehensive and multidisciplinary, encompassing:
Conclusion
Neonatal respiratory distress is defined by abnormal respiratory rate and work of breathing—making it one of the most frequent reasons for neonatal intensive care admission. Its causes can be classified into pulmonary and extrapulmonary etiologies, often arising from disrupted postnatal transition due to risk factors like prematurity, cesarean delivery, maternal diabetes, hypoxia, or infection. Prompt diagnosis through clinical assessment, laboratory testing, and imaging guides tailored management, ranging from oxygen therapy and ventilatory support to surfactant replacement, targeted medications, and surgical intervention.


