Infantools_Ventilation

Oxygen Therapy

Learning outcomes

  • Oxygen therapy: evaluate the indications for oxygen therapy and the risks of hyperoxia-induced tissue injury.
  • Monitoring: compare pulse oximetry versus arterial blood gas analysis in titrating targeted oxygen delivery.

Introduction

Oxygen therapy must be dynamically adjusted to current physiological needs to prevent both hypoxia and hyperoxia:

  • hypoxic injury (particularly to cerebral tissue)
  • hyperoxia (reactive oxygen species and inflammatory cascade)

Because preterm neonates have an immature antioxidant defense system, the oxidative stress compromises ongoing organ development, contributing to bronchopulmonary dysplasia (BPD) in the lungs and retinopathy of prematurity (ROP) in the retina. Oxygen delivery must therefore be carefully adjusted, with continuous pulse oximetry serving as the primary bedside standard among available methods for monitoring blood oxygenation.

Pulse oximetry

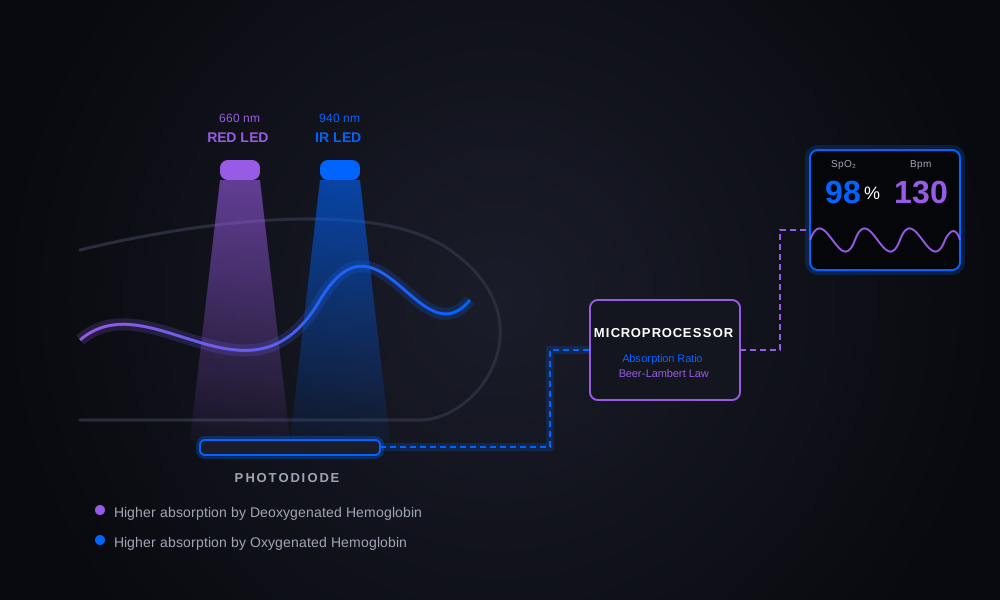
A pulse oximeter sensor consists of a pair of light-emitting diodes (LEDs) positioned opposite a photodiode across a translucent neonatal site—typically the palm, finger, or the wrist/ankle in newborns of lower gestation. One LED emits red light (660 nm), while the other emits infrared light (approximately 940 nm).

Pulse oximetry relies on the differential wavelength absorption of hemoglobin depending on its oxygenation status – oxygenated hemoglobin absorbs more infrared light, whereas deoxygenated hemoglobin absorbs more red light. To isolate each signal and compensate for ambient light interference, the LEDs cycle rapidly in sequence (red on, infrared on, then both off). The photodiode measures the transmitted red-to-infrared light ratio, which is converted into a visual saturation reading using the Beer–Lambert law.

Key points of pulse oximetry:
  • measures Saturation of peripheral Oxygen (SpO2)
  • non-invasive, painless and continuous method
  • less precise than direct measurement of arterial oxygen saturation (SaO2)
  • cannot detect hyperoxemia once saturation reaches 100% 👉 strict, gestational-age-adjusted upper SpO2 limits to prevent oxygen toxicity (esp. in preterm infants)
Oxygen_therapy
Principles of pulse oximetry: calculating SpO₂ via red and infrared light absorption ratios.

The arterial partial pressure of oxygen (PaO2) measures the amount of oxygen gas dissolved in arterial blood plasma, offering the most precise assessment of a neonate’s respiratory gas exchange. Obtained via direct arterial blood gas analysis, it serves as the clinical gold standard for diagnosing true hypoxemia and hyperoxemia. Unlike pulse oximetry, PaO2 accurately identifies hyperoxemic states, making it essential for safely titrating oxygen therapy and preventing oxidative injury in vulnerable preterm infants.

Key points of arterial partial pressure of oxygen:

  • measures Pressure (arterial blood) of Oxygen (PaO2)
  • invasive, painful and non-continuous method
  • part of arterial blood gas analysis: normal values 8-10 kPa in term infants; 6-9 kPa in preterm infants
  • detects both hypoxemia and hyperoxemia

Oxygen therapy

Therapeutic oxygen must have appropriate pressure and flow (flowmeter, reduction to decrease the oxygen source pressure). Source oxygen usually comes from the central oxygen supply system in the hospital or mobile oxygen gas cylinders. Regarding home oxygen therapy, liquid oxygen is being used (portable oxygen concentrator).

Oxygen must be warmed-up and humidified to maintain thermal neutrality (risk of hypothermia) and fluid balance (risk of dehydration) for the newborn. Dry oxygen gas can damage respiratory epithelium and lung tissue.

Oxygen application methods:

  • short-term inhalation (connecting tube, resuscitation bag connected to oxygen)
  • medium-term inhalation (incubator, nebulizer)
  • long-term inhalation (ventilator with flowmetry, oxygen concentration measurement (FiO2 0.21 = 21% oxygen), nasal cannula with low-flow oxygen)

Conclusion

Neonatal respiratory distress is defined by abnormal respiratory rate and work of breathing—making it one of the most frequent reasons for neonatal intensive care admission. Its causes can be classified into pulmonary and extrapulmonary etiologies, often arising from disrupted postnatal transition due to risk factors like prematurity, cesarean delivery, maternal diabetes, hypoxia, or infection. Prompt diagnosis through clinical assessment, laboratory testing, and imaging guides tailored management, ranging from oxygen therapy and ventilatory support to surfactant replacement, targeted medications, and surgical intervention.


References

  • Sweet DG, Carnielli VP, Greisen G, et al. European Consensus Guidelines on the Management of Respiratory Distress Syndrome: 2025. Neonatology. 2026;123(4):514-539. doi:10.1159/000551062

More articles from Infantools

  • Resuscitation

    Perinatal asphyxia remains one of the most common indications for postnatal resuscitation. The necessary prerequisites for successful resuscitation are properly equipped rooms (delivery suite, neonatal wards with the right and functional equipment; warmed up to the temperature of 26 °C) with properly trained personnel. Ventilation (and circulation dysfunction) are indications to initiate resuscitation…

  • Congenital heart defects

    Critical congenital heart defects (CCHD) present during the neonatal period with cyanosis and/or cardiac failure depending on the particular defect and its severity. The incidence of the CCHD is approximately 1-3 : 1000. These defects can be diagnosed antenatally, however, anomaly scan detection rates vary significantly among different countries and also within the same country (e.g. 33-70% prenatal CCHD diagnosis in…

  • Early onset sepsis

    Early onset sepsis (EOS) is an infectious complication in newborns that have clinical presentation within the first 72 hours of life. Sometimes also called perinatal due to pathogenesis – vertical transmission shortly before the birth (transplacental), ascendent infection from the cervicovaginal space (chorioamnionitis, funisitis, fetal infection) or during the vaginal delivery. The pathogen can be also the cause…

  • Persistent ductus arteriosus

    Persistent ductus arteriosus (PDA) connects aorta with main pulmonary artery (MPA) (or left pulmonary artery – LPA) and during fetal life serves as important right-left shunt => mixed blood flowing from the pulmonary artery to the descendant aorta and supplying the lower half of the body. PDA prenatally remains open due to low partial pressure…

  • Intraventricular hemorrhage

    The intraventricular hemorrhage in the preterm infants usually originates in the germinal matrix (temporary developmental structure with significant vascular supply due to massive mitotic and metabolic activity). The structure is divided from the cerebral ventricles only by a thin layer of subependymal cells and disappears after 34 weeks of gestation – one…

  • Bronchopulmonary dysplasia

    Bronchopulmonary dysplasia (BPD) or chronic lung disease (CLD) is a typical disease of extremely low birth weight infants (ELBW; birth weight < 1000g) who experienced adverse lung development but were not necessarily exposed to mechanical ventilation (“new” BPD). Originally, BPD was linked to acute respiratory failure (of various origins) and prolonged mechanical…

Leave a Reply

Your email address will not be published. Required fields are marked *

This site is protected by reCAPTCHA and the Google Privacy Policy and Terms of Service apply.

